

aNTIMICROBIAL rESISTANCE
1 in 4 Americans Have Exaggerated or Made Up Symptoms to Try to Get Antibiotics
Nov. 5, 2026
Misrepresenting symptoms to get antibiotics is dangerous. The results show an urgent need to develop better communication strategies for doctors and patients.
More than a quarter of Americans have exaggerated or made up symptoms to try to get antibiotics from their doctor, either for themselves or for their children, a new study has found.
The survey of nearly 1,000 people nationwide uncovered common motivations for misrepresenting symptoms, including feeling very sick or needing to return to work or school.
The results indicate an urgent need for better communication between doctors and patients, so that patients can be confident that their symptoms are taken seriously and treated appropriately—whether or not that means antibiotics.
“Now that we have a clearer picture of how common these behaviors are and the reasons behind them, the next step is to look at strategies that help patients express their preferences and communicate what they’re feeling to their provider, and for their provider to hear them, understand their concerns, and reassure them,” says Alistair Thorpe, PhD, research assistant professor of population health sciences at University of Utah Health and one of the first authors on the study.
Among survey respondents, 28% said that they had deliberately misrepresented disease symptoms to try to get antibiotics for themselves. A similar proportion, 27%, said that they had misrepresented symptoms to get antibiotics for a child in their care. This included cases in which a symptom was exaggerated or entirely made up.
People most commonly misrepresented symptoms because they felt very sick, or felt that their child was very sick, and believed that antibiotics were the only treatment that would work.
“It is a tough situation,” Thorpe says. “People are experiencing unpleasant symptoms, and they can have this strong feeling that antibiotics are the only thing that can help them feel better. Being told to just rest and wait is a hard thing to do, and if you think there’s something that could make you feel better, it’s a very hard impulse to override.”
Other respondents mentioned that they or their child needed to recover quickly to return to work or school, or cited a desire to control their own treatment path.
Misrepresenting symptoms to get antibiotics is dangerous, the researchers explain. Antibiotics are effective and important treatments for bacterial infections but do nothing against viral infections—the most common cause of cold- or flu-like symptoms. And like any medication, antibiotics have a risk of side effects.
“These medications are not totally benign for the patient,” explains Andrea Levy, PhD, professor of social sciences at Connecticut State Community College Middlesex and one of the first authors on the study. “And antibiotic use contributes to increasing antimicrobial resistance, which is a broader public health concern.”
That means it’s crucial for doctors to have a complete, accurate picture of patients’ symptoms in order to prescribe antibiotics when they’ll help—and avoid prescribing them when they might harm.
The researchers emphasize that the goal of this research is not to blame people for misrepresenting symptoms. “There are very understandable reasons that we can sympathize with about why patients might feel the need to misrepresent symptoms, or why caregivers might do so on behalf of their children,” Levy says. “We’re simply saying: perhaps there’s a better way.”
Patients’ reasons for misrepresenting symptoms are often grounded in past experiences. People were more likely to overstate symptoms if they had had their symptoms dismissed or downplayed by a doctor in the past, for instance.
If someone has been incorrectly prescribed antibiotics for a prior viral infection, it can also lead to a powerful association between antibiotics and feeling better, Thorpe adds. Viral infections usually clear up on their own, and it’s easy for people to incorrectly credit their body’s healing to antibiotics.
The results show a need for better communication strategies for both doctors and patients, the researchers say. Doctors need ways to address patients in ways that make it clear that they are heard and that their symptoms are being taken seriously, even when antibiotics wouldn’t help.
“Going forward, it will be important to test different ways to change the communication patterns between patients and their clinicians,” says Angela Fagerlin, PhD, professor and chair of the Department of Population Health Sciences at U of U Health and senior author on the studies. “How can clinicians communicate to patients the importance of not prescribing antibiotics when they won’t be effective, how can patients communicate in a way that their concerns and needs are met, and how can we help each other better understand the others’ perspectives?”
“The practical takeaway is not for clinicians to become more suspicious of their patients,” Levy says. “Instead, clinicians need to create interactions where caregivers and patients feel heard enough that they don’t feel the need to exaggerate in order to be taken seriously.”
“Patients regularly feel this way,” Thorpe adds. “It should be a priority for us to identify strategies for reassuring people, re-earning trust, and finding the right ways to address their concerns. We want a long-term relationship between a patient and health care provider to be based on trust, openness, transparency, and people having each other’s best intentions in mind.”
The results were published in JAMA Network Open as “Symptom Misrepresentation to Obtain Antibiotics” and “Caregiver Symptom Misrepresentation to Obtain Antibiotics in Pediatric Encounters.”
Source: University of Utah Health
CDC’s 2026 AR Threats Report: What the New Burden Estimates Mean for Infection Prevention and Environmental Hygiene
Oct. 27, 2026
Nineteen drug-resistant bacteria and fungi cause an estimated 9.7 million infections and 50,800 deaths in the United States each year, according to the 2026 update to the Centers for Disease Control and Prevention (CDC)’s Antimicrobial Resistance Threats Report, released today. The agency describes the update as its most comprehensive estimate to date of the toll that drug-resistant pathogens take on human health in this country.
The statistical uncertainty around those headline figures is wide: CDC puts the plausible range at 8.2 million to 11.7 million infections and 39,400 to 65,100 deaths annually, based on 2023 data. Even at the low end, the numbers underscore what infection preventionists and environmental services (EVS) professionals see every day: resistance is not a distant or hypothetical threat, and much of it is transmitted through the hands, surfaces, and water systems of the healthcare environment.
The 2026 update is delivered as an interactive online data platform. It offers individual and combined burden estimates for each pathogen, a Watch List of emerging threats, patient stories, summaries of CDC’s response activities, and downloadable data and graphics.
Four tiers of threat
CDC sorts the 19 pathogens into three threat levels, plus a Watch List of six organisms whose U.S. burden is not yet well understood.
Urgent threats require urgent and aggressive action: Candida auris, carbapenem-resistant Acinetobacter, carbapenem-resistant Enterobacterales (CRE), and drug-resistant Neisseria gonorrhoeae.
Serious threats require prompt and sustained action. This tier holds 13 pathogens: Clostridioides difficile, drug-resistant Campylobacter, drug-resistant Candida, drug-resistant Mycobacterium tuberculosis, drug-resistant Neisseria meningitidis, drug-resistant nontyphoidal Salmonella, drug-resistant Salmonella Typhi, drug-resistant Shigella, drug-resistant Streptococcus pneumoniae, extended-spectrum cephalosporin-resistant Enterobacterales (ESC-RE), methicillin-resistant Staphylococcus aureus (MRSA), multidrug-resistant Pseudomonas aeruginosa, and vancomycin-resistant Enterococcus (VRE).
Concerning threats require careful monitoring and prevention: clindamycin-resistant group B Streptococcus and drug-resistant group A Streptococcus.
The Watch List includes azole-resistant Aspergillus fumigatus, drug-resistant Bordetella pertussis, drug-resistant dermatophytes, drug-resistant Haemophilus influenzae, drug-resistant Mycoplasma genitalium, and nontuberculous mycobacteria (NTM).
CDC assigns threat levels using seven factors: clinical impact, economic impact, current U.S. incidence, projected change in incidence over five years, transmissibility, preventability, and the availability of effective treatments. Preventability explicitly includes pathogen-specific infection control recommendations and the barriers to implementing them at scale — a reminder that how well a pathogen can be stopped at the bedside and in the environment shapes how CDC ranks it.
The healthcare heavy hitters
The pathogens most closely tied to healthcare settings account for the large majority of deaths in the report. The table below shows CDC’s 2023 estimates for those organisms, ordered by deaths.
| Pathogen | Threat level | Infections/cases (2023) | Deaths (2023) | Costs (2023) |
|---|---|---|---|---|
| ESC-RE | Serious | 293,299 | 13,886 | $2.29 billion |
| C. difficile | Serious | 412,504 | 11,339 | $6.42 billion |
| MRSA | Serious | 220,997 | 7,499 | $1.56 billion |
| VRE | Serious | 65,204 | 6,536 | $725 million |
| Drug-resistant Candida | Serious | 33,596 | 1,681 | Not estimated |
| MDR P. aeruginosa | Serious | 18,939 | 1,588 | $538 million |
| CRE | Urgent | 14,878 | 1,252 | $174 million |
| Carbapenem-resistant Acinetobacter | Urgent | 9,497 | 817 | $355 million |
| C. auris | Urgent | 4,523 clinical cases | Not estimated | Not estimated |
Source: CDC, U.S. Burden Estimates for AR Threats Report Pathogens, 2023. Point estimates shown; CDC publishes 95% intervals for each.
A simple sum of these deaths — removing CRE, which CDC folds into the ESC-RE estimate — comes to roughly 43,000, or about 85% of the report’s 50,800 total. Their combined attributable costs approach $12 billion a year, with C. diff alone accounting for more than half. These are rough editorial tallies rather than CDC figures, since CDC’s own aggregation adjusts for overlap and uncertainty in ways a straight sum cannot.
Several of these organisms are notable for how lethal they are relative to their case counts. VRE is linked to about one death for every 10 infections, carbapenem-resistant Acinetobacter and CRE to roughly one in 12. By comparison, drug-resistant Streptococcus pneumoniae causes the most infections of any pathogen in the report — about 2.6 million — but far fewer deaths, at 3,734.
C. diff moves from urgent to serious
The most significant category change in the 2026 update is a prevention success story. CDC reclassified C. diff from an urgent to a serious threat, citing in part the impact of infection prevention efforts, particularly in healthcare settings, where the agency has measured declining case counts since 2011.
That is not a signal to stand down. C. diff still accounts for an estimated 412,504 cases, 11,339 deaths, and $6.4 billion in costs each year — the highest price tag of any pathogen in the report by a wide margin. CDC notes it remains among the most common causes of healthcare-associated infections in hospitals, and that community-associated cases are even more numerous.
The new estimates also capture more of the problem than past reports did. Previous editions counted only hospitalized C. diff cases; the 2026 update adds non-hospitalized cases. CDC says continued infection control and appropriate antibiotic use remain essential to sustaining progress. For EVS teams, that means the sporicidal disinfection, terminal cleaning, and monitoring programs that form part of that prevention effort are what keep C. diff from climbing back into the urgent tier.
C. auris: still climbing
C. auris is the one pathogen for which CDC says the 2026 numbers can be compared with earlier reports, and the trend is unambiguous. Clinical cases rose by more than 50% from 2022 to 2023 and have increased nearly tenfold since 2019. Screening cases, detected in colonized patients without symptoms, rose nearly 50% in 2023, partly because more facilities are screening.
Resistance is spreading across drug classes. In 2023, 96% of tested C. auris samples were resistant to fluconazole and 16% to amphotericin B. Echinocandin resistance, which undermines the recommended first-line treatment, was seen in 1% of samples but is increasing. Isolates resistant to all three major antifungal classes have been detected, though rarely.
For environmental hygiene professionals, the C. auris profile is a familiar one. Colonized patients shed the fungus onto surfaces and objects around them, and those surfaces become a route to the next patient. CDC lists hand hygiene, gowns and gloves, and cleaning with disinfectants approved for C. auris as effective controls, especially when started at or before the first detected case.
The report’s C. auris case study shows what that looks like in practice. After Mississippi identified its first locally acquired case in November 2022, the state health department worked with seven facilities and found gaps in staff training, access to approved disinfectants, and communication during patient transfers. Addressing them was followed by a 78% drop in new clinical cases over the next three months.
What’s new — and why not to compare
Readers tempted to set the new totals against figures from earlier editions should resist. CDC states that its methods and data sources changed substantially for every pathogen except C. auris, and that direct comparisons between reports should not be made.
Several definitions were broadened, which by itself raises some estimates:
- ESC-RE replaces the former ESBL-producing Enterobacteriaceae category and now also includes Enterobacter species and Klebsiella aerogenes.
- Group A and group B Streptococcus now include non-invasive as well as invasive infections. The group A category was renamed from erythromycin-resistant to drug-resistant to reflect rising resistance to both macrolides and clindamycin.
- C. diff now includes non-hospitalized cases.
One pathogen joined the main list: drug-resistant Neisseria meningitidis, added as a serious threat. Three joined the Watch List: drug-resistant dermatophytes, drug-resistant Haemophilus influenzae, and nontuberculous mycobacteria. NTM’s addition will interest anyone managing healthcare water systems, given the organisms’ association with plumbing and biofilm.
The environment is part of the transmission story
Alongside the report, CDC published a transmission overview mapping how each threat most commonly spreads across community, healthcare, food, animal, and environmental pathways. Its healthcare section names three routes EVS and infection prevention teams know well: contaminated surfaces such as bedrails, the hands of healthcare workers, and sinks and drains that splash organisms onto nearby surfaces. It also notes entry through surgery and devices such as catheters and ventilators.
That framing matters for how facilities allocate resources. CDC’s seven-factor threat assessment weighs preventability — including the reach of infection control recommendations and the barriers to adopting them. Several of the deadliest organisms in the report, including CRE, carbapenem-resistant Acinetobacter, MDR P. aeruginosa, VRE, and C. auris, persist in the healthcare environment and move between patients through surfaces, hands, and water.
Practical takeaways for EVS and infection prevention leaders include:
- Treat disinfectant selection as pathogen-specific. CDC’s C. auris guidance calls for products approved against that organism, and the Mississippi response found facilities lacked access to them.
- Invest in training and competency. Staff training was one of the gaps Mississippi’s health department identified before cases fell sharply.
- Bring sinks and drains into the cleaning program. CDC explicitly identifies them as a route by which resistant organisms reach patients.
- Close the loop on transfers. Communicating a patient’s resistant-organism status between facilities was another gap addressed in the Mississippi response.
- Sustain what is working. The C. diff reclassification shows that consistent prevention moves the numbers, and that the gains depend on keeping it up.
The report’s message for the environmental hygiene workforce is that the cleaning cart and the disinfectant label are part of the nation’s antimicrobial resistance strategy, not adjacent to it.
Resources
The full report, pathogen fact sheets, and downloadable data and graphics are available at arpsp.cdc.gov/artr. CDC’s broader antimicrobial resistance resources are at cdc.gov/antimicrobial-resistance.
- AR Threats Report home
- All pathogens by threat level, methods, and changes since the last report
- U.S. burden estimates table, 2023 (PDF)
- Candida auris pathogen page
- How AR threats spread (PDF)
Reference: Centers for Disease Control and Prevention. Antimicrobial Resistance Threats Report. U.S. Department of Health and Human Services. October 27, 2026. https://arthreats.cdc.gov
SHEA Publishes Resource to Help Hospitals Build the Business Case for Diagnostic Stewardship
Sept. 11, 2026
The Society for Healthcare Epidemiology of America (SHEA) has published a new resource describing how diagnostic stewardship can improve patient outcomes, strengthen hospital quality metrics, and reduce healthcare costs.
Business Case for Diagnostic Stewardship: A Practical Guide from the Society for Healthcare Epidemiology of America (SHEA) Diagnostic Stewardship Special Interest Group, published in Antimicrobial Stewardship and Healthcare Epidemiology (ASHE), provides healthcare leaders with a framework for developing institution-specific business cases for diagnostic stewardship programs, including financial models for five high-impact interventions.
As an example, the authors estimate that a representative 200-bed community hospital implementing all five interventions could generate approximately $2.5 million to $2.8 million in annual laboratory and clinical savings. Depending on a hospital’s baseline performance, improved quality metrics could also reduce CMS Hospital-Acquired Condition penalties by an estimated $200,000 to $600,000. The interventions may also improve publicly reported healthcare-associated infection metrics and hospital reputation.
Diagnostic stewardship ensures the right test is ordered for the right patient at the right time and that results are appropriately interpreted. The paper examines five common opportunities for improvement:
- Optimizing Clostridioides difficile testing
- Optimizing urine culture use
- De-implementing unnecessary procalcitonin testing
- Optimizing respiratory pathogen panel use
- Optimizing blood culture use
For each intervention, the authors outline implementation strategies, projected financial impact, and practical examples that hospitals can adapt to their own settings.
“Healthcare leaders know that every investment must improve both patient care and operational performance,” said Sarah E. Turbett, MD, senior author of the paper. “This framework helps hospitals evaluate and implement diagnostic stewardship in ways that improve clinical outcomes, strengthen quality metrics, and demonstrate measurable value.”
The publication comes as diagnostic excellence receives increasing national attention. The CDC’s Core Elements of Hospital Diagnostic Excellence identifies diagnostic stewardship as a key strategy for improving diagnosis while advancing healthcare quality, safety, and value-based care.
The paper was developed by SHEA’s Diagnostic Stewardship Special Interest Group to help healthcare executives, laboratory leaders, infection prevention professionals, antimicrobial stewardship teams, and clinicians develop institution-specific business cases for diagnostic stewardship initiatives.
Source: Society for Healthcare Epidemiology of America (SHEA)
Widely used early warning score may help guide the urgency of antibiotic treatment for suspected sepsis
Aug. 20, 2026
A study of nearly 100,000 adults treated for suspected infection suggests that the National Early Warning Score (NEWS2), a score based on routinely collected vital signs that is widely used to identify patients at risk of clinical deterioration, may help clinicians identify which patients are most likely to benefit from immediate antibiotic treatment and which may safely undergo further evaluation before receiving antibiotics. NEWS2 has been adopted by many healthcare systems internationally and is recommended in the United Kingdom to help guide the urgency of antibiotic treatment in suspected sepsis, but until now there has been little empirical evidence supporting this approach.
The study, led by investigators from the Center for Sepsis Epidemiology & Prevention Studies (SEPSIS) at the Harvard Pilgrim Health Care Institute, appears in The Lancet Respiratory Medicine on August 5.
Refining Urgent Treatment Decisions in Sepsis
While timely administration of antibiotics is a cornerstone of sepsis care, diagnosing sepsis early can be complicated because its symptoms often overlap with many other serious medical conditions. Many patients treated for possible sepsis ultimately have non-infectious illnesses, exposing them to antibiotics that may offer limited benefit while increasing the risk of adverse effects and antibiotic overuse.
Recognizing the need to balance timely treatment with diagnostic uncertainty, international sepsis guidelines have evolved from recommending immediate antibiotics for all patients with suspected sepsis toward prioritizing patients with septic shock, where the evidence suggests treatment delays have the greatest impact on survival. However, it has remained unclear whether septic shock alone is sufficient to identify all patients who may benefit from immediate antibiotics.
“The challenge with sepsis is that clinicians must decide whether to give antibiotics right away before they know with certainty whether a patient has a serious bacterial infection,” says Chanu Rhee, Harvard Medical School associate professor at the Harvard Pilgrim Health Care Institute and lead author of the study. “Our study suggests that NEWS2, a simple early warning score based on routinely measured bedside parameters, can help identify the patients most likely to benefit from immediate treatment—including many beyond those with septic shock— while allowing clinicians greater confidence to take additional time evaluating lower-risk patients.”
Researchers analyzed electronic health record (EHR) data from nearly 100,000 adults treated for suspected infection in emergency departments at nine U.S. hospitals between 2015 and 2024. They examined how the relationship between antibiotic timing and survival varied according to NEWS2 scores and the presence or absence of septic shock. To the researchers’ knowledge, this is the first large study to compare two international strategies for guiding the urgency of antibiotic treatment in suspected sepsis — the United Kingdom’s National Institute for Health and Care Excellence (NICE) recommendation to use NEWS2 to guide the urgency of antibiotic treatment in patients with suspected sepsis, alongside the Surviving Sepsis Campaign’s emphasis on septic shock.
Key Findings
- Earlier Antibiotics Were Associated with Improved Survival in the Highest NEWS2 Category: Among patients with NEWS2 scores of 7 or higher, each additional hour to antibiotic treatment was associated with increased mortality.
- NEWS2 Identified Additional Patients Beyond Septic Shock: Many patients with NEWS2 scores of 7 or higher did not have septic shock but still showed an association between antibiotic delays and worse outcomes.
- No Survival Association at Lower NEWS2 Scores: Among patients with lower NEWS2 scores, earlier antibiotic treatment was not associated with improved survival.
- Potential to Better Guide the Urgency of Antibiotic Treatment: NEWS2 may offer a more comprehensive framework than septic shock alone for determining which patients warrant the most urgent antibiotic treatment.
“One of the most important unanswered questions in sepsis has been whether there is a better way to determine which patients are most likely to benefit from immediate antibiotics than relying on septic shock alone,” said Michael Klompas, Professor of Population Medicine at Harvard Medical School and senior author of the study. “Our findings suggest that NEWS2 may provide an objective and practical way to identify those patients using a simple bedside score that is already routinely used in clinical practice.”
The researchers note that the study was observational and cannot prove that earlier antibiotic treatment directly caused differences in survival. Additional studies in other healthcare settings will be important to confirm the findings.
Source: Harvard Pilgrim Health Care Institute
Research Targets Drug-resistant Bacteria
Aug. 20, 2026
Researchers at the University of Texas at Arlington have received more than $4.6 million in federal funding to study how harmful bacteria become resistant to antibiotics and how they interact with the body during infection. By understanding how bacteria adapt under stress, the findings could lead to improved treatments and better protection against dangerous infections.
Qing Tang, assistant professor of biology and head of the Tang lab, recently secured two major federal grants:
- A five-year, $2.05 million grant from the National Institute of General Medical Sciences for a project titled “Bacterial stress responses mediated by c-di-AMP.”
- A five-year, $2.65 million grant from the National Institute of Allergy and Infectious Diseases for a project titled “Bacterial modulation of host metabolism and immunity during infection.”
“Our lab studies two important human pathogens, Listeria monocytogenes and Staphylococcus aureus. We are interested in how these bacteria respond to stress during infection and during antibiotic treatment,” Tang said. “My belief is that fundamental research can lead to therapies that help patients in the long term.”
The pathogens studied in Tang’s lab can cause serious illnesses, including meningitis and listeriosis from Listeria monocytogenes and chronic lung infections in people with cystic fibrosis from Staphylococcus aureus. The research comes as antibiotic-resistant infections become increasingly difficult to treat. According to the Centers for Disease Control and Prevention, drug-resistant bacteria pose an “urgent threat” to public health.
Understanding how bacteria survive the body’s immune defenses and antibiotic treatment, and identifying new ways to stop them, is a driving force behind Tang’s research.
“What drives me is that scientists can focus on specific questions and discover new pathways and mechanisms that may later become drug targets or lead to new treatments for disease,” Tang said. “I also like training students and young scientists because it takes generations of scientists working together to understand how diseases occur and how to treat them. Passing that knowledge on is important for improving public health.”
Source: University of Texas at Arlington
Many Countries Overusing Powerful Antibiotics, Study Says
July 23, 2026
Many countries are using too many powerful and inappropriate antibiotics, fueling antibiotic resistance concerns, while millions lack access to the specific drugs they need. That is according to a major international study of antibiotic use published today in The Lancet Public Health.
Research led by City St George’s, University of London and University of Oxford developed the first global framework that estimates how many and which type of antibiotics each country needs to treat their infections.
Antibiotics are grouped by the World Health Organization (WHO) into three categories, known as the “AWaRe” system:
- ‘Access’ antibiotics are used for most common infections and have a lower resistance risk.
- ‘Watch’ antibiotics have a broader spectrum, are used for specific infections and come with higher safety and resistance concerns.
- ‘Reserve’ antibiotics are last resort antibiotics used to treat multi-drug resistant infections.
In 2024, world leaders at the United Nations agreed that at least 70% of antibiotic use worldwide should come from the Access group by 2030. However, no method previously existed to determine the right balance of antibiotics for any individual country.
To address this, researchers analyzed global data from 186 countries, territories and areas (CTAs), representing 99.8% of the global population. They grouped these countries into ‘peer groups’ based on similar infection burdens, resistance patterns, socioeconomic characteristics and healthcare access.
Within each group, countries with the lowest antibiotic use and the fewest infection-related deaths were used as benchmarks to determine what optimal antibiotic use should look like for similar countries. They then estimated optimal levels of Access, Watch and Reserve antibiotics required in each setting based on infection and resistance burdens.
The team calculated that in 2019, around 43 billion days of antibiotics were needed globally, averaging out to roughly one antibiotic course per person per year, to treat all bacterial infections appropriately. They found that 77% of global antibiotic use should be Access antibiotics, suggesting the UN’s 70% target is reasonable.
Although higher-income countries currently use the most Watch and Reserve antibiotics, the study estimates that more than 80% of the world’s optimal need for these medicines lies in lower-income countries, where infectious disease and antimicrobial resistance burdens are highest.
The researchers then compared their estimates with real-world antibiotic use data from 67 countries where this data was available. Nearly three-quarters (72%) of countries analyzed were using more antibiotics in total than needed, and almost every country (99%) prescribed too many Watch antibiotics, which contribute the most to antibiotic resistance. Worryingly, 60% of countries were still using antibiotics that the WHO considers should no longer be prescribed.
At the same time, 42% of countries were using fewer Access antibiotics than estimated optimal levels, and more than half (52%) were not using enough Reserve antibiotics than estimated to be needed. This means patients with life-threatening drug-resistant infections might not be receiving the specific treatments they need.
The findings suggest that many countries could improve antibiotic use by reducing unnecessary Watch antibiotic prescribing while increasing access to essential Access antibiotics, and ensuring availability of Reserve antibiotics for patients with highly resistant infections.
Aislinn Cook, lead author and Senior Research Fellow in Infectious Diseases Epidemiology at City St George’s, University of London, and DPhil student at Nuffield Department of Primary Care Health Sciences, University of Oxford said, “Our findings show the world faces a double challenge – while some antibiotics are being overused, millions of people may still lack access to the medicines they need to treat their infections. We have developed the first practical way for countries to estimate how much of each type of antibiotic their populations need based on infection burden and antibiotic resistance. This framework can help move the conversation beyond measuring antibiotic consumption to matching antibiotic use with public health need. This can support countries to develop more targeted policies to reduce overuse while ensuring sustainable access to effective antibiotics.”
The team emphasize that improving access to antibiotics for the most vulnerable populations will require action at both local and national levels. This includes ensuring that quality-assured antibiotics are available and affordable in frontline healthcare settings, while national governments ensure that the right antibiotics are procured and supplied in sufficient quantities. The researchers also highlight the need for better monitoring of antibiotic use to identify areas of overuse and underuse, and for national targets based on local data that align antibiotic use more closely with public health and clinical need.
Dr. Koen Pouwels, associate professor in health economics, Nuffield Department of Primary Care Health Sciences, University of Oxford and co-author, said, “Global targets such as aiming for 70% of antibiotic use to come from the WHO Access group are an important starting point, but they cannot tell countries how much of each AWaRe antibiotic group they actually need. By providing country-specific benchmarks, our work gives policymakers a practical way to move beyond percentage targets and make better-informed decisions about reducing overuse, improving access and strengthening antibiotic stewardship. Importantly, these benchmarks can become more ambitious over time if countries reduce infection burden, even in the face of demographic change.”
The Case for Fewer Antibiotics in Joint Replacement Surgery
July 1, 2026
For anyone undergoing a total hip or knee replacement, the goal is a smooth recovery and a return to pain-free movement. However, a possible risk from these procedures is periprosthetic joint infection.
Infections are leading causes of joint replacement failures, often requiring additional surgeries, prolonged hospital stays, as well as emotional and financial strain on patients. For higher risk patients, such as individuals with diabetes, chronic kidney disease, or a history of tobacco use, many orthopedic surgeons prescribe an extended course of oral antibiotics for an additional week after the patient leaves the hospital.
A Yale study published in The Journal of Arthroplasty found that this extra week of medication may not be needed.
A decade-long study tracking thousands of patients revealed that extended oral antibiotics did not significantly lower the risk of joint infections following hip or knee replacement surgery.
The research team found that the infection rates between those who received the regimen of oral antibiotics and those who did not were nearly identical at both the 90-day mark and one year after surgery. Even when researchers isolated the highest-risk patients, the extra medication provided no measurable benefit.
“For years, the instinct in medicine has often been to provide an extra layer of protection, assuming that more antibiotics equals less risk,” says Daniel Wiznia, MD, an associate professor who specializes in hip and knee joint reconstruction and the study’s principal investigator. “However, this research prompts us to step back and re-evaluate our routine protocols. If an extra week of medication isn’t moving the needle on infection rates, we need to identify other treatments that might have an impact.”
Wiznia’s team looked back at existing medical records, tracking adult patients who underwent joint replacements between 2015 and 2025.
To ensure a fair comparison among patients, they used a statistical technique called propensity matching. Because surgeons usually give extended antibiotics to sicker or more vulnerable patients, comparing the two groups directly would skew the data. Propensity matching allowed the researchers to pair each patient who received extended antibiotics with four similar patients who did not, balancing them precisely by age, biological sex, and overall health status.
The findings remained consistent. Even when analyzing patients with morbid obesity, which is a condition that significantly raises the risk of surgical complications, the extended antibiotics failed to offer further protection.
This outcome challenges several previous, smaller studies suggesting that extended antibiotics were a cost-effective benefit for high-risk individuals, according to Wiznia. Instead, it aligns with recent national database trends indicating that standard, immediate post-operative care is already doing the heavy lifting.
Ilda Molloy, MD, MS, co-author on this research paper, assistant professor, and another Yale orthopedic surgeon who specializes in hip and knee joint reconstruction, agrees.
“At Yale, prosthetic joint infection management is a multidisciplinary effort that brings together orthopedic surgery, infectious diseases, microbiology, pharmacy, nursing, and other key clinical teams,” Molloy says. “These findings reinforce that infection prevention is about developing coordinated, evidence-based protocols that address risk before, during, and after surgery while using antibiotics thoughtfully and responsibly.”
In her role as director of prosthetic joint infection prevention and policy with Yale New Haven Health System, Molloy works across medical specialties to develop and evaluate infection prevention procedures, ensures that complex decisions incorporate the perspectives of multiple clinical disciplines, and refines protocols based on emerging evidence.
Standard care at Yale, where this study took place, includes thorough nasal screenings, antiseptic skin wipes, and precisely timed intravenous antibiotics right before and after the incision is made.
“What this tells us is that our primary, immediate infection-prevention measures are incredibly robust,” Wiznia explains. “The work we do in the operating room and in the immediate hours following surgery is the real baseline of defense. Adding more oral antibiotics on top of that foundation later appears to offer diminishing returns.”
While the study did not find a dramatic spike in immediate complications from the extra medication such as severe allergic reactions or kidney damage, the lack of benefit raises broader medical concerns. Public health experts and the Centers for Disease Control and Prevention have long warned about the dangers of over-prescribing antibiotics, which can lead to antibiotic resistance and impact healthy gut bacteria.
“Previous projections suggest that implementing extended antibiotics nationwide for all high-risk joint patients could add 50,000 years of cumulative antibiotic exposure annually,” Wiznia adds. “This massive inflation increases the risk of opportunistic infections like Clostridium difficile, a severe and painful bacterial infection of the colon.”
Fortunately, the patients in this study did not show a statistically significant surge in these adverse events. But as clinicians, researchers, and surgeons look at the big picture, prescribing a medication that offers no proven benefit introduces unnecessary long-term risk and cost.
The research team emphasized that, while these findings are powerful, they come from a retrospective look at data, which can occasionally be limited by missing administrative codes or variations in how patients actually take their pills at home as prescribed.
According to Wiznia, the medical community will need trials in which patients are randomly assigned to groups ahead of time to collect more conclusive data.
In the meantime, this research serves as a reminder that more medication does not always mean better outcomes.
“Every medication we prescribe should have a clear, proven purpose,” Wiznia says. “Our goal shouldn’t be to just give blanket prescriptions to everyone categorized as ‘high-risk.’ We need to refine our precision, looking at specific biomarkers like blood sugar control or nutritional levels, so we can treat the individual rather than the statistic.”
Source: Yale School of Medicine
New Antibiotic Design Could Help Treat Drug-resistant Infections
June 1, 2026
A new way of designing antibiotics could support the discovery of new treatments for drug-resistant infections.
It could also help revive antibiotics that have lost effectiveness because bacteria have evolved over time to survive the drugs meant to kill them.
The study, led by researchers at King’s College London and published in the Journal of Medicinal Chemistry, describes a new approach called ‘Efflux Resistance Breaker’, or ERB, which is designed to overcome one of the ways bacteria escape antibiotic treatment.
Many bacteria use molecular pumps, known as efflux pumps, to push antibiotics out of the cell before the drugs can reach levels high enough to kill them. This reduces the amount of antibiotic inside the bacteria and allows resistant infections to survive.
The King’s-led team has shown that antibiotics can be chemically redesigned so they are less easily removed by these pumps. This allows the antibiotic to remain inside the bacterial cell at higher concentrations, restoring its ability to kill bacteria even when resistance mechanisms are present.
Importantly, the work shows that the ERB approach could support a new way of developing antibiotics by building resistance-breaking properties directly into their design.
Unlike previous strategies that have tried to combine antibiotics with separate efflux pump inhibitors, this new approach builds resistance-breaking properties directly into the antibiotic molecule. This means the antibiotic is designed to protect itself from being pumped out.
Khondaker Miraz Rahman, a professor of medicinal chemistry from King’s College London, who led the study said:
“Antimicrobial resistance is rising, but the number of truly new antibiotics in development remains worryingly low. Our work shows that we can redesign antibiotics so they stay inside bacterial cells at higher concentrations and overcome resistance mechanisms that would normally make them ineffective. This approach could help us design better new antibiotics, but it could also help revive existing antibiotic classes that bacteria have learned to defeat.”
Professor J. Mark Sutton, from the UK Health Security Agency, who is a key collaborator on this project said:
“Efflux pumps are a major cause of antibiotic resistance because they reduce the concentration of drug inside the bacterial cell. This study shows that rational chemical design can be used to overcome that problem. By building efflux resistance directly into the antibiotic, we may be able to restore activity against bacteria that are no longer controlled by current drugs.”
The study provides an important proof of concept for antibiotic discovery. It shows that maintaining high intracellular antibiotic concentration can help overcome resistance, including in bacteria that already show reduced susceptibility to existing antibiotics.
The researchers believe the ERB platform could be used as a general strategy to design antibiotics with built-in resilience to efflux-mediated resistance. The manuscript describes ERB technology as a framework for developing next-generation antibiotics and for revitalizing existing drugs.
The team will now focus on commercializing the ERB technology and advancing antibiotics developed using this strategy towards clinical development, with the aim of translating this discovery into new treatment options for drug-resistant infections.
Source: King’s College London
CDC Releases Antibiotic Use and Stewardship in the United States, 2025 Update: Progress and Opportunities
Key takeaways from this CDC report:
- Antibiotic stewardship is the effort to ensure that antibiotics are prescribed and used when they provide a clear health benefit.
- Improving antibiotic use is a key strategy to optimize patient safety and combat antimicrobial resistance in the United States.
This annual report provides an overview of CDC’s surveillance data on antibiotic use, along with guidance and example collaborations aimed at improving antibiotic use to optimize patient safety across all areas of healthcare.
In 2014, the Centers for Disease Control and Prevention (CDC) released the Core Elements of Hospital Antibiotic Stewardship to outline structural and procedural components associated with successful antibiotic stewardship programs. Since then, the Core Elements have been adapted to different healthcare settings and specific implementation strategies have been identified, including small and critical access hospitals and dialysis settings. The Core Elements framework has also been used to support hospital programs to improve healthcare quality in other areas, such as hospital sepsis programs and diagnostic excellence.
In 2016, CDC published the Core Elements of Outpatient Antibiotic Stewardship as a framework for clinics and clinicians to improve antibiotic prescribing in outpatient settings. Increasingly, outpatient care is provided under the umbrella of a health system.
In 2026, CDC will update the Outpatient Core Elements to focus on the role health system leadership can play in supporting the development and expansion of outpatient antibiotic stewardship programs within their networks. This updated guidance is applicable to all outpatient settings, including those with limited stewardship capacity and infrastructure, and aligns with published evidence and recommended best practices. For example, health systems can disseminate treatment recommendations based on national guidelines for common outpatient infections. Treatment recommendations can be integrated into the clinical workflow using clinical decision support tools embedded into electronic health records. The updated Core Elements guidance standardizes antibiotic stewardship implementation to improve the quality and consistency of outpatient care.
Antibiotic use and stewardship data
The Antimicrobial Use (AU) Option of the National Healthcare Safety Network (NHSN) is a resource for U.S. acute care hospitals to monitor and compare their antibiotic use data to other facilities. As of January 1, 2025, 4,362 acute care hospitals across the United States have submitted at least one month of data to the NHSN AU Option. While it is anticipated that the remaining hospitals in the United States will be onboard in 2025, hospitals that are already enrolled will continue to report to the NHSN AU Option to fulfill a Centers for Medicare & Medicaid Services (CMS) Promoting Interoperability Program measure requirement.
The Standardized Antimicrobial Administration Ratio (SAAR) is a risk-adjusted summary measure available to hospitals participating in the NHSN AU Option. The SAARs were updated using 2023 data, and additional facilities and patient care locations were included. The 2024 AU Option Data Report features the updated SAAR data and provides a summary of SAAR distributions and antibiotic use for each SAAR category across adult, pediatric, and neonatal patient care locations. Data are also reported annually on the Antimicrobial Resistance and Patient Safety Portal, allowing users to explore and visualize SAAR distributions at both national and state levels.
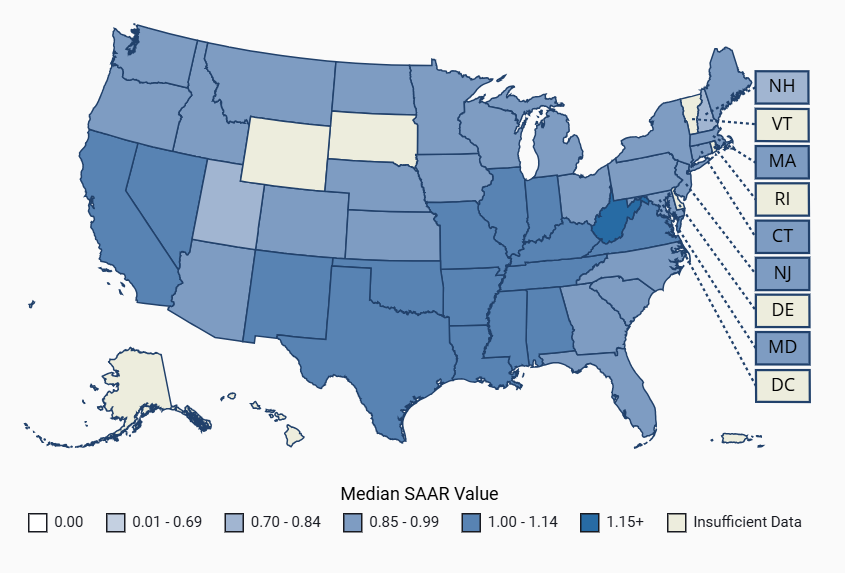
SAAR data by state reporting all for adults in 2023
This map displays 2023 median SAAR values for all SAAR agent categories and SAAR populations.
Hospital Antibiotic Stewardship Core Elements and priorities
The implementation of antibiotic stewardship core elements in acute care hospitals is assessed through the NHSN Patient Safety Component Annual Hospital Survey. Hospital staff complete annual survey questions that assess the uptake of CDC’s Core Elements. CDC reports the percentage of hospitals meeting the Core Elements by year and state. In 2024, the percentage of hospitals meeting all 7 core elements was 97%.
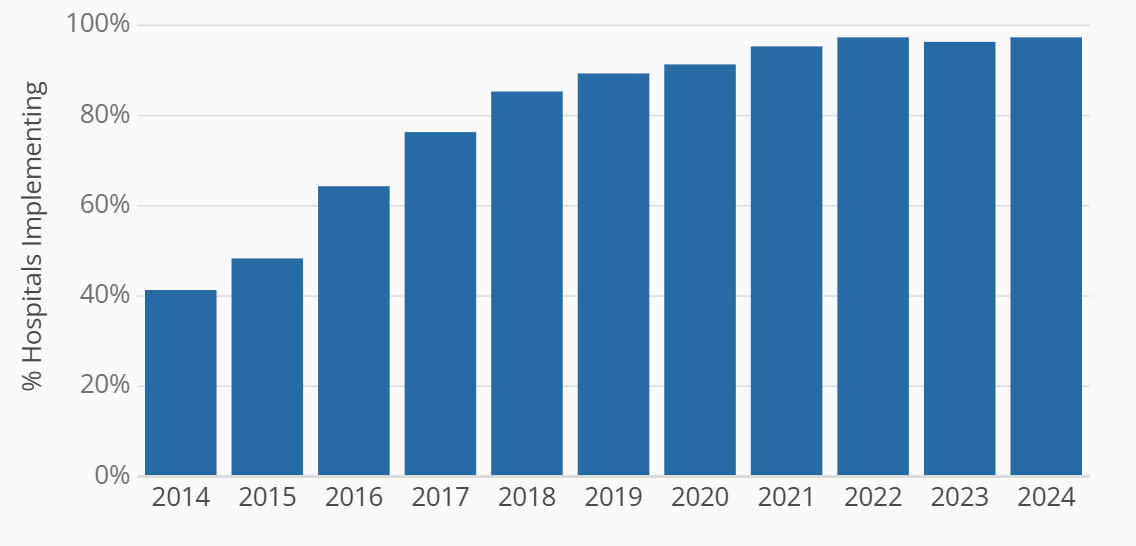
Changes over time in Hospital Antibiotic Stewardship
This graph shows the proportion of U.S. hospitals reporting seven Core Elements from 2013-2024.
With robust national uptake of the Core Elements, CDC released Priorities for Hospital Core Element Implementation (Priorities) in Fall 2022 to enhance the quality and impact of hospital stewardship programs. In 2024, the percentage of hospitals meeting all six Priorities was 16% and hospitals meeting five of the six Priorities was 36%.
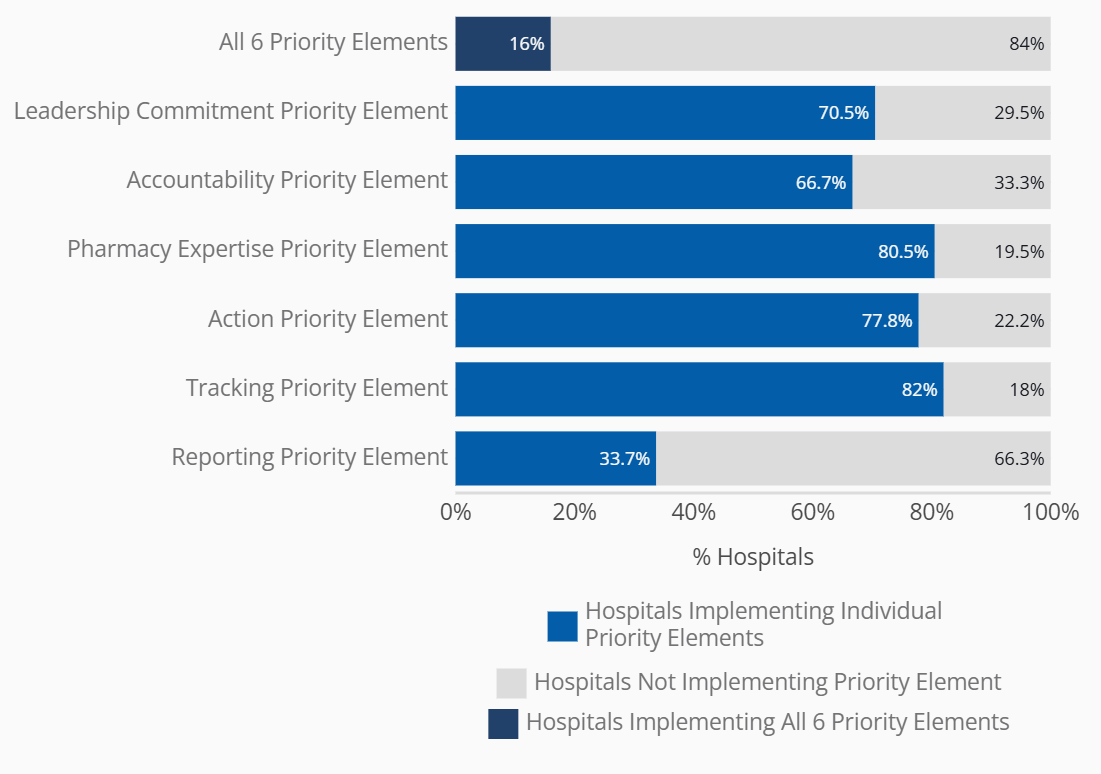
Hospital Antibiotic Stewardship implementation by Priority Element
This graph shows the proportion of U.S. hospitals reporting each priority element in 2024
Core Elements of Antibiotic Stewardship
At a glance
- Antibiotic stewardship is the effort to measure and improve how antibiotics are prescribed by clinicians and used by patients.
- CDC’s Core Elements of Antibiotic Stewardship offer providers and facilities a set of key principles to guide efforts to improve antibiotic use and, therefore, advance patient safety and improve outcomes.
Overview
Improving antibiotic prescribing practices and use is critical to effectively treat infections, protect patients from harms caused by unnecessary antibiotic use, and combat antimicrobial resistance.
The Core Elements frameworks complement existing guidelines and standards from key healthcare partner organizations, including the Infectious Diseases Society of America, Society for Healthcare Epidemiology of America, American Society of Health System Pharmacists, Society of Infectious Diseases Pharmacists, and The Joint Commission.
CDC recognizes that there is no “one size fits all” approach to optimize antibiotic use for all healthcare settings. The complexity of medical decision-making surrounding antibiotic use and the variability in facility size and types of care in U.S. healthcare settings require flexible programs and activities.
Core Elements
Core Elements of Hospital Antibiotic Stewardship Programs
A framework for implementing antibiotic stewardship in hospital settings.
Core Elements of Outpatient Antibiotic Stewardship
A framework for implementing antibiotic stewardship in outpatient settings.
Core Elements of Antibiotic Stewardship for Nursing Homes
A framework for implementing antibiotic stewardship in nursing home settings.
Core Elements of Human Antibiotic Stewardship Programs in Resource-Limited Settings
A framework for implementing antibiotic stewardship in resource-limited settings.
Core Elements of Antibiotic Stewardship for Health Departments
A framework for implementing antibiotic stewardship in health departments.
Source: CDC